
Greek for simple
Healthcare. Powered by AI.
Simple for members. Smarter where it matters.
Find care. Understand your benefits. Get answers.
And let Aplos AI optimize how your healthcare gets priced.

Ask Mariah
What can I help you with?
Find the provider.
Optimize the price.
You choose the provider that’s right for you. Aplos works behind the scenes to identify the lowest-net-cost pricing path available for that care.
You choose
Provider
Aplos AI
Analyzes available pricing paths
Lowest net cost
Best available pricing for that provider
Ask Mariah
AI-powered healthcare search
Find providers, understand benefits and get answers using natural language.
AI pricing optimization
One provider. Multiple ways to price it.
Aplos AI evaluates available pricing pathways to identify the lowest net cost for the provider selected.
Provider selected→AI pricing→Lowest net cost
One intelligence layer
across all of your healthcare.
Medical
Evaluates available network, direct-contract and alternative reimbursement options to identify the lowest available net cost.
Prescription drugs
Evaluates available pharmacy, manufacturer and alternative sourcing options to identify the lowest available net cost.
One objective: Lowest Net Cost.
Provider selected by the member
Aplos evaluates available pricing paths
Lowest net cost
Healthcare doesn't have one price.
Aplos finds the best available pricing path.
Better healthcare economics
without restricting provider choice.
Traditional plans rely primarily on a single contracted network price. Aplos evaluates multiple available pricing paths to determine how care can be priced more efficiently.
More provider flexibility.Smarter pricing.Simpler member experience.
One platform.
Three better experiences.
For employers
Control healthcare cost without making employees navigate a narrower healthcare experience.
Learn more →For brokers
A differentiated health plan combining provider flexibility, AI and intelligent pricing.
Learn more →For members
Find care, understand your benefits and get answers without learning how healthcare works behind the scenes.
Learn more →Have a healthcare question?
Ask Mariah.
Your ID card, claims, deductible and provider search all live in the member portal.
How it works
One agreement. Every line item still visible.
A health plan is only as simple as the connections inside it. Aplos built those connections first — so what reaches an employer is one plan, and what reaches a member is one experience.
What’s under the agreement
What makes Aplos one plan?
Every self-funded plan needs these same pieces. The difference isn’t which ones Aplos picked — it’s that they were already connected, tested and running before your group ever arrived.
-
Administration
Eligibility, claims, plan documents, banking, reporting and run-out — the record everything else reads from and writes to.
-
Medical access
Aplos uses an open access network. There is no restricted list of providers — members can see any provider they choose.
-
Pharmacy
Transparent pharmacy benefits, with rebates passed through to the plan. The pharmacy team looks for a lower price on every fill rather than waiting for the member to ask.
-
Specialty medication
High-cost and infused medications are sourced and delivered to the member or the office giving them, with nationwide infusion coverage — often at no cost to the member.
-
Member support
One team and one number for benefits, claims, finding a provider, pharmacy questions and billing. Navigation and balance-bill defense are part of the plan, not another thing to buy.
Open access, nationwide
Coverage that travels with the member.
An open access network means what it sounds like. There is no approved-provider list to check, no referral to chase, and no one to ask for permission before making an appointment.
Members choose their own doctors, and coverage works the same way in another state as it does at home.
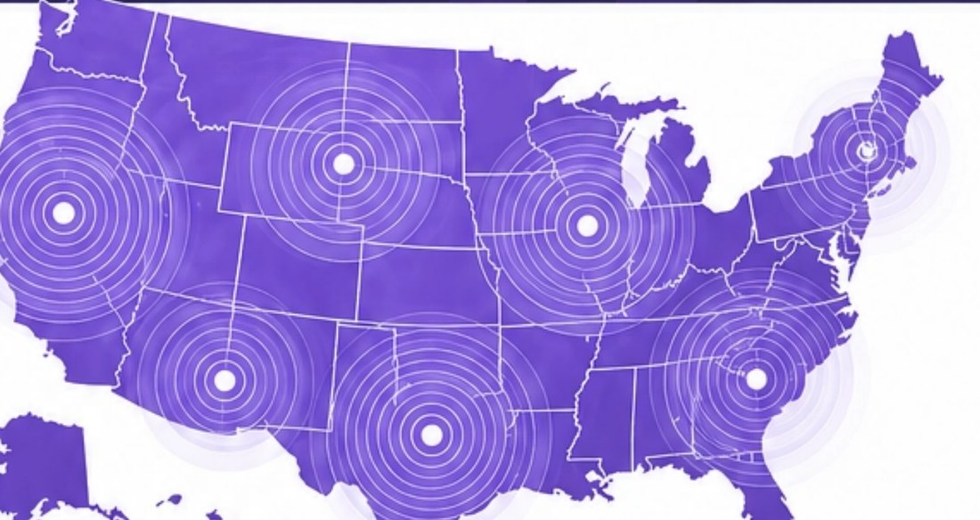
Open access coverage, nationwide.
The part that usually breaks
The data flows are already established and tested.
Selecting good vendors is the easy half. The half that consumes an implementation is getting them to talk to each other — and to keep talking after go-live. These are the feeds that have to work, every day, in the right order:
Feed 01
Eligibility
Who is covered today, at the pharmacy counter and the front desk — not who was covered at last month's file drop.
Feed 02
Claims
Priced medical claims moving back into the system of record so the plan pays once, correctly, and reporting reconciles.
Feed 03
Accumulators
Deductible and out-of-pocket totals shared between medical and pharmacy, so a member never satisfies the same deductible twice.
Feed 04
Pharmacy
Fills, prior authorizations and specialty sourcing flowing between the pharmacy benefit and the medical benefit without a member in the middle.
When these are built from scratch for one employer, they are the reason a January 1 effective date slips. Aplos runs them on flows that are already live for other groups.
Assembled, not bundled
Where the two are different
This distinction matters more than it sounds. A bundle normally buys convenience by hiding what each piece costs.
| A typical bundle | Aplos | |
|---|---|---|
| Contracting | One agreement | One agreement |
| Pricing | One all-in rate — component cost isn't visible | Each component priced on its own line |
| Reporting | Rolled up | Reported separately, so you can see which component is producing the savings |
| Integration | Usually yours to build | Already built, already running for live groups |
| Pharmacy rebates | Often retained in part | 100% passed through to the plan |
| Unspent claim dollars | Depends on the funding arrangement | Claim dollars the plan does not spend stay with the employer |
| Stop-loss | Usually bundled in, priced out of sight | We quote it, or you place it — your call |

Complicated behind the scenes.
Simple where it matters.
For members
Welcome to your Aplos health plan.
Healthcare doesn't have to be complicated. Aplos is designed to give you access to high-quality care while making your experience simpler, more transparent, and easier to navigate. Here's what that means on an ordinary Tuesday.
Getting care
What you actually do
-
Go where you want. See who you want.
There's no list to check first and no narrow network to stay inside. Keep the doctors you already have, or choose someone new. If you'd rather not choose alone, call us and we'll find someone and set the visit up for you.
-
Know before you go.
Search in your own words — "knee MRI", "my shoulder hurts" — and provider search comes back with real prices for the providers near you, so the cost isn't a surprise that arrives six weeks later.
-
Show your Aplos card and pay your share
That’s it. You don’t have to check a list, chase a referral, or work out whether someone counts as in network.
Same procedure, three providers, three prices — you pick with the number in hand. Provider names and prices shown are illustrative.
Provider search, in the member portal
One call
One number reaches the same team every time.
Benefits. Claims. Finding a provider. A prescription. A bill you don't understand. You don't have to work out who handles what — the team that answers already has your plan in front of them.
888-77-APLOS
The number printed on your member ID card.
Your member ID card
A digital copy is in your portal the moment you log in, and a printed card is mailed when your coverage starts. Everything a front desk or a pharmacy needs is on it.

Payer ID 36338
Hoffman Estates, IL 60195
Sample card · your group’s details will differ

Keep your doctor. Know your cost.
Get on with your life.
What's included
The rest of your plan

Your prescriptions
Your plan uses a transparent pharmacy benefit manager, so the price you see is the real price. Your pharmacy team checks for a lower option every time — a different pharmacy, a different form of the same drug, a manufacturer program — instead of waiting for you to ask.
High-cost and specialty medication
If you're prescribed a specialty or infused drug, it's sourced through a dedicated program and shipped to you or to the office giving it to you — often at no cost to you. You don't arrange any of that; the pharmacy team does.
Virtual doctor visits
See a clinician from home, usually the same day. Good for the things that don't need an exam room — a rash, a refill, a sick child at 9pm — without paying for a clinic visit to get an answer.
Your hospital bill gets a second look
Nonprofit hospitals are required to offer financial assistance to patients who qualify. Aplos screens your hospital claims, files the application on your behalf, and the discount comes off before the plan pays.
Primary care
Direct primary care is an additional Aplos component, available regionally. Where it’s part of your plan, you get unlimited visits, routine labs and around-the-clock urgent care at no cost at the point of care. Check your plan materials — or ask Mariah — to see whether you have it.

In your pocket
Your plan, on your phone
The member portal is where your card, your claims and your care team live.
Mariah OnlineHealth benefits and coverages
Virtual assistants can make mistakes.
Check important information.
Ask Mariah anything
She reads your plan documents, so the answer is your group’s answer — and a real person is one tap away.
High-Cost Specialty Rx
Sourced, coordinated and delivered — at no cost to eligible members.
Specialty Rx, handled
Start a specialty prescription, message the pharmacy team, and track the shipment to your door.
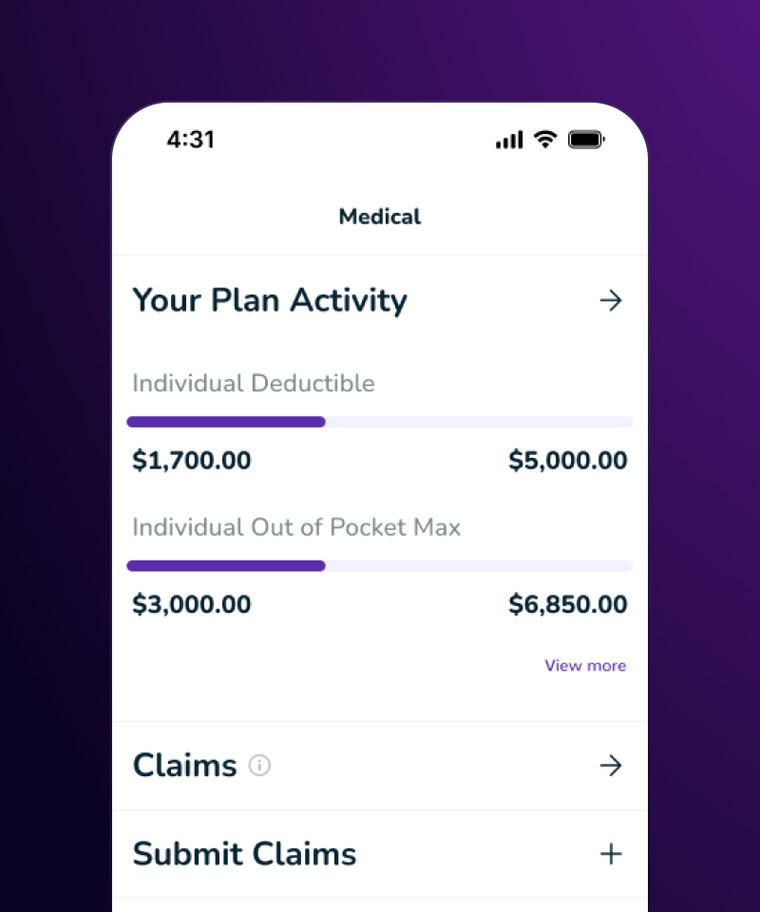
Track your claims
See where you stand on your deductible and out-of-pocket max, follow a claim through, and submit one yourself.
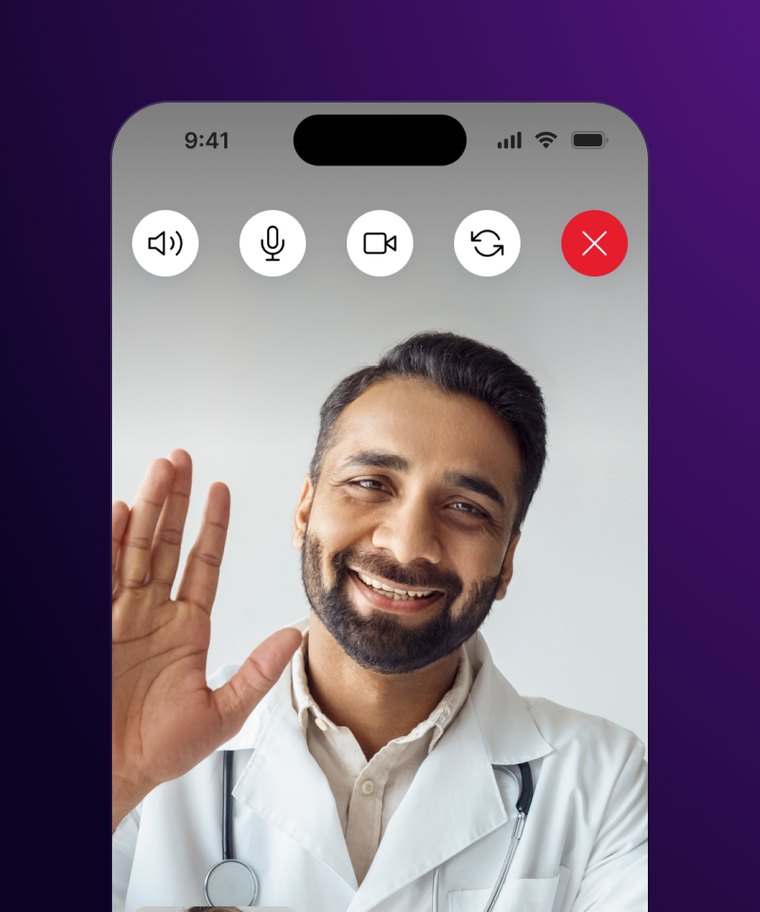
See a doctor from anywhere
Start a virtual visit when a trip to the clinic isn’t worth it — evenings and weekends included.
Just ask Mariah.
Your Aplos guide to simpler healthcare.
Member questions
Things people ask us most
Do I have to stay in a network?
A provider's office says they don't take my plan. What now?
How do I know what something will cost before I go?
Where is my ID card?
Can I see a doctor without going in?
What happens with an expensive hospital bill?
Who do I call — the plan, the pharmacy, or the doctor's billing office?
For employers & brokers
All the pieces.
Already working together.
The assembly is already done. Aplos is a self-funded health plan delivered as a single program for groups that want real savings without handing their people a narrow network — and without spending an implementation season wiring vendors together.
For the broker
You keep the client. We do the assembly.
One proposal, one implementation, and a plan your client can actually understand at renewal. Aplos can quote stop-loss and bring back quotes from our preferred carrier partners, or you place it yourself — whichever gets the group the better outcome.
You deliver Aplos to your clients
You bring the plan, you stay in the renewal conversation, and the advice stays yours. We are the program under the plan, not a competing advisor.
One implementation, not many
Eligibility, claims, accumulator and pharmacy feeds are already established and tested. You're connecting a group to running flows, not commissioning new ones.
Nothing hidden in an all-in rate
Every component is priced and reported on its own line, so you can defend each one in a renewal meeting and show a client where savings actually came from.

Better benefits shouldn’t require a more complicated plan.
You don’t need a stack of vendors. You need one plan that works.
For the employer
What the program returns to the plan
These are program figures drawn from the current book, not a projection for any particular group. What a specific group sees depends on its census, its claims history and its plan design — which is exactly what a proposal is for.
Employer savings
20–40%
Typical employer savings against a conventional fully insured or network-based arrangement.
Pharmacy rebates
100%
Passed through to the plan. No spread pricing, no retained rebate.
Unspent claim dollars
Stay put
Claim dollars the plan does not spend stay with the employer, not with a carrier.
Open access coverage, nationwide — no narrow network for members to stay inside.
Common objections, answered plainly
The questions that decide the case
Isn't this just a bundle with the pricing hidden?
What about stop-loss?
My group is small. Is there a floor?
Won’t members hate this kind of plan?
How long does implementation take?
Can we keep our current network or carve something out?
Getting a number
What a proposal needs from you
Two documents get you a real comparison rather than a brochure.
A current census
Ages, genders, ZIP codes and tier. No names needed.
Claims experience
Twenty-four months where it exists, plus any large-claimant detail your current carrier will release.
Current plan documents and renewal
So the comparison is against what the group actually has, not a generic benchmark.
A worked example
Where the savings
actually come from.
Every program in this market quotes a percentage. Far fewer will show you the arithmetic underneath it. Below is a real employer’s claims year, repriced line by line — what was billed, what a conventional arrangement paid, and what each Aplos component would have taken out.
The group
One year. Forty-three thousand claims.
A self-funded manufacturer, referred to here as ABC Company. We took twelve months of their actual medical and pharmacy claims and repriced every one of them as though Aplos had been the plan — same care, same providers, same members.
Billed charges
$22.9M
What providers charged across the period, before any discount is applied.
Claims repriced
43,193
Every claim in the period, not a sample and not the large ones only.
Savings identified
$7.02M
Medical and pharmacy combined, against what the plan actually paid.
Medical · $5,309,440
A discount off a billed charge is not the same as a low price.
A conventional network sells its discount — here, roughly 42% off billed charges. Aplos prices each claim against a published, defensible benchmark instead, which produced a materially lower allowed amount on the same claims. Two further strategies then come off what remains.
| Medical claims | Conventional network | Aplos open access network |
|---|---|---|
| Billed charges | $22,941,239 | $22,941,239 |
| Effective discount | 42.2% | 60.3% |
| Net allowed | $13,259,088 | $9,107,672 |
| Charity-care screening | Not applied | −$550,306 |
| No Surprises Act negotiation | Not applied | −$607,718 |
| What the plan pays | $13,259,088 | $7,949,648 |
How $13.26M becomes $7.95M
Each bar is what the plan still owes after that step. Nothing here depends on a member choosing a different hospital.
Pharmacy · $1,709,651
Eight percent of the prescriptions. Seventy percent of the money.
This is the shape of almost every pharmacy benefit, and it is why a formulary argument about generics misses the point. A small number of high-cost fills drives the spend, so that is where the sourcing work goes.
3,335 fills out of 43,193.
The same 3,335 fills.
What the program does with them
Those high-cost fills are routed through the high-cost specialty medication program rather than an ordinary retail channel — manufacturer assistance, alternative sourcing pathways and therapeutically equivalent options are each checked before the plan pays retail.
What it returned
39.12%
$1,709,651 off pharmacy spend, net of rebate weighting and program fees — on the same prescriptions, for the same members.
$467,741 of it never
reached a member’s mailbox.
Savings that land on the employer are only half the job.
The part employers ask about second
Members were not asked to work for this.
None of the savings above depend on a member driving further, choosing a different hospital, or navigating anything. The repricing happens on the claim. The charity-care application is filed on their behalf. The balance-bill negotiation happens between Aplos and a billing office, with the member left out of it.
The $467,741 figure is the member share of the result — out-of-pocket amounts that went away rather than moving onto someone’s kitchen table.
Where a member would have felt it
A hospital bill they qualified to have reduced
Screened and filed for, rather than left to the member to discover.
A surprise bill from a provider they never chose
Negotiated under the No Surprises Act before it became their problem.
A specialty prescription they couldn’t afford to fill
Sourced through the program, frequently at no cost to the member.
Read this before you quote it
What this analysis does and doesn’t say.
It is a retrospective repricing
These are real claims from a real employer, repriced as though Aplos had been in place. They are not a realized result and we don’t present them as one. No group was live on Aplos while these claims were incurred.
It is one group, not an average
Savings of this shape depend on the claims underneath them — the provider mix, the drug mix, and how concentrated the spend is. Another group’s year would produce a different bridge.
It excludes stop-loss and fees
The figures compare claim cost to claim cost. Your proposal will show administration and program fees on their own lines, and stop-loss priced separately, so you can compare like for like.
The employer is not named here
Their claims experience is their own. We will walk a specific group and their broker through the underlying detail under NDA rather than publishing it.
The only number that matters to you
Run this on your own claims.
The analysis above took a census and two years of claims. We will do exactly the same thing with yours and show you the bridge for your group — not a percentage from somebody else’s book.
A current census
Ages, genders, ZIP codes and tier. No names needed.
Claims experience
Twenty-four months where it exists, plus large-claimant detail.
Current plan documents and renewal
So the comparison is against what you actually have.
For providers & billing offices
Yes — you can see this patient.
Aplos members are covered by a self-funded employer health plan. There is no narrow network and no referral requirement. If your system doesn't recognize the plan name, the information below is what your billing office needs.
Claims & eligibility
Where to send a claim
Submit electronically using the payer ID below, or by mail. Eligibility and benefits are confirmed by phone at the same number your patient uses.

| Payer ID (EDI) | 36338 |
| Paper claims | Aplos Health Plans P.O. Box 95600 Hoffman Estates, IL 60195 |
| Eligibility & benefits | 888-77-APLOS |
| Claim status | 888-77-APLOS |
| General inquiries | info@aplos.health |
Provider questions
What billing offices ask
We're not in your network. Can we still see the patient?
How will the claim be priced?
Do you require prior authorization?
Can we verify eligibility electronically?
A patient was prescribed a specialty or infused drug.
Who do we contact about a payment we disagree with?

About
Aplos.
Greek for simple.
That is the whole promise — healthcare for living, not figuring out. A health plan should be understandable by the person carrying the card and defensible by the person who bought it, and it should take up as little of anyone’s week as possible.
The Aplos idea
Healthcare is complicated.
Your health plan doesn’t have to be.
The complexity is real and it isn’t going away. Claims price a dozen different ways, drugs are sourced through channels nobody outside the industry has heard of, and every vendor speaks a different file format. None of that is the member’s problem to solve, and it shouldn’t be the employer’s either.
So we took the complicated part and finished it. Four structural things make the difference, and each one removes a decision somebody would otherwise have to make.
One agreement instead of six
Administration, medical access, pharmacy, specialty pharmacy and member support are contracted together, with the data flows between them already built and tested. The employer signs once and implements once — the integration work that usually lands on a benefits manager is already done.
One number instead of a phone tree
Benefits, claims, finding a provider, a pharmacy problem, a bill nobody understands — the same team answers all of it, with the plan already in front of them. Nobody has to work out which vendor owns the question.
No network to memorize
There is no narrow network and no list to check first. Members keep the doctors they have. Pricing is decided claim by claim, so being “in network” stops being the member’s problem to solve.
Nothing hidden in one rate
Simple does not mean opaque. Each component stays separately priced and separately reported, so an employer can see which piece is producing savings — and which one isn’t — and change it without unwinding the whole plan.

Healthcare changes throughout life.
Simple shouldn’t.
Aplos takes care of the complicated so you don’t have to.
The Aplos model
Ten things that come standard
This is the whole plan, in the order a member tends to meet it. Everything here is included in the program unless it is marked otherwise.
-
PPO-free navigation
No narrow network to stay inside, and provider search returns real prices before a visit is booked.
-
Direct primary careRegional · optional
An additional Aplos component where we have clinic coverage: unlimited visits, routine labs and 24/7 urgent care at no cost at the point of care.
-
Transparent, unbundled plan design
Every component priced and reported on its own line — never rolled into a single rate.
-
Transparent PBM
Pass-through pharmacy pricing with 100% of rebates returned to the plan. No spread.
-
High-cost drug sourcing
Specialty medications above $300 are sourced through a dedicated program, often at no cost to the member.
-
White-glove member support
One team and one number for benefits, claims, providers, pharmacy and billing.
-
50-state infusion program
Nationwide infusion coverage for J-code management, so a member is never sent out of area.
-
20–40% employer savings
Program figures from the current book — a specific group’s result depends on its census and claims.
-
Fiduciary-friendly architecture
Built so a plan sponsor can show what was paid, to whom, and why.
-
Aligned incentives across every partner
Compensation tied to total cost of care or documented savings — never to billed charges.
Why we built it
Built around people.
Not the system.
Self-funding gives an employer control, transparency and the upside of a good claims year. What it also gives them, if nobody has solved it, is a set of vendors who have never exchanged a file before and a benefits manager in the middle of them.
Aplos exists because that middle job shouldn’t belong to the employer. We assembled the components, built and tested the data flows between them, and kept every piece separately priced so nothing is hidden inside a single rate.
How we talk about ourselves
Assembled, not bundled
One agreement. Every line item still visible.
Employer-tested. Employee-approved.
Both halves have to be true or neither one counts.
Invisible to the member
The complexity is real. It just isn’t the member’s problem.
The savings stay put
Claim dollars the plan doesn’t spend stay with the employer.
What we don't say
We would rather be precise than impressive.
We don't say "guaranteed savings"
We say claim dollars the plan does not spend stay with the employer. That's the mechanism, and it's true every year.
We don't say "one all-in rate"
Each component is priced and reported on its own line. An all-in rate is the thing we built the program to avoid.
We don't say "no disruption"
Changing a health plan moves something for somebody. We would rather name what moves, and show what we do about it, than promise nobody notices.
Healthcare made simple. Life made better.
Talk to us about a group, or ask a question about a plan you already have.
Contact
Talk to a person.
Not a call center. Not another vendor. Your Aplos team. Members, call the number on your card and you’ll reach the same people every time — everyone else, the form below reaches us directly.
Send us a note
Tell us who you are and we'll route it to the right person rather than an inbox.
Direct lines
| Members | 888-77-APLOS |
| Providers | 888-77-APLOS |
| info@aplos.health | |
| Claims payer ID | 36338 |
| Mailing address | Aplos Health Plans P.O. Box 95600 Hoffman Estates, IL 60195 |

The team that answers 888-77-APLOS
Member login
Your plan, in one place.
Your ID card, your deductible and out-of-pocket totals, your claims, provider search with real prices, and a direct line to your care team.
Trouble signing in? Call 888-77-APLOS — the same team that handles your benefits can get you in.

One number. One team.
Real answers.
Setting up your account
Start at the member portal
Use the sign-in button above, or go to aplos.health and choose Member Login.
Enter your Aplos group code
It's on your welcome letter and on the back of your member ID card. If you can't find it, call us and we'll read it to you.
Verify and set a password
You'll confirm your date of birth and the email or phone your employer has on file, then choose a password.